Pain lasting three months or longer can come from an abdominal organ, the abdominal wall, an irritated nerve, the spine, or the sympathetic nervous system, and those sources require different tests and treatments. You will learn which warning signs need emergency care, how clinicians narrow down the pain generator, and when a specialized block or multidisciplinary plan is appropriate.
Key takeaways
- Seek emergency care for sudden severe pain, rigid abdomen, fainting, or vomiting blood.
- Track pain location, triggers, bowel changes, medicines, and previous test results.
- Match a nerve block to the nerves and pain pattern identified during evaluation.
- Set treatment goals around the underlying condition, function, sleep, and safe pain control.
Which abdominal pain symptoms need emergency care first?
Sudden severe abdominal pain needs emergency assessment before you arrange a chronic-pain consultation. Seek prompt care for these warning signs:
| Symptom or sign | Why it matters | What to do |
|---|---|---|
| Sudden severe abdominal pain, a rigid abdomen, or a swollen abdomen | Possible perforation, appendicitis, bowel obstruction, or another acute surgical problem | Go to an emergency department |
| Vomiting blood or black stools | Possible gastrointestinal bleeding | Seek emergency care immediately |
| High fever, persistent vomiting, jaundice, or fainting | Possible infection, obstruction, organ dysfunction, dehydration, or internal bleeding | Obtain urgent medical assessment |
| Pregnancy-related pain or bleeding | Possible ectopic pregnancy or another pregnancy complication | Seek emergency obstetric or emergency care |
Do not use a specialized pain assessment as a substitute for investigating appendicitis, bowel obstruction, perforation, gastrointestinal bleeding, infection, ectopic pregnancy, or other acute conditions. A pain procedure before diagnosis could delay treatment or obscure a worsening problem.
When you seek care, report when the pain began, its severity, exact location, and associated symptoms. Tell the clinician whether pregnancy is possible, whether you recently had surgery, and which medicines, including anticoagulants and painkillers, you currently take.
How do clinicians identify the actual source of chronic abdominal pain?
A useful assessment starts by mapping the pain, not by ordering every test. Eating or bowel movements suggest visceral pain; movement, posture, scars, prior operations, urination, or a history of shingles point toward abdominal-wall, post-surgical, nerve, urinary, or referred spinal causes. Burning, electric shocks, numbness, allodynia, or pain from light touch suggests neuropathic involvement.
1. Take a detailed history, including timing, location, triggers, bowel and bladder symptoms, menstrual or pregnancy possibility, shingles, operations, scars, injections, and current medicines. Back pain, a dermatomal pattern, or pain altered by spinal movement supports referred spinal pain; sweating, flushing, temperature change, or vascular symptoms can suggest sympathetic involvement.
2. Examine the abdomen and nervous system. Carnett’s sign supports abdominal-wall pain when tenderness stays the same or increases as you tense the abdominal muscles. A small trigger point near the rectus edge, altered sensation, or movement-related pain raises concern for anterior cutaneous nerve entrapment syndrome.
3. Review medicines and order targeted blood and urine tests, with pregnancy testing when relevant. These help identify infection, inflammation, anaemia, urinary disease, metabolic problems, or medication-related pain.
4. Use ultrasound for selected abdominal, pelvic, or urinary questions; CT for acute or structural organ disease; MRI for spine, soft-tissue, pelvic, or nerve evaluation; and endoscopy for suspected gastrointestinal lining disease.
5. Refer to gastroenterology, gynaecology, urology, neurology, surgery, or pain specialists when findings require expertise. Normal ultrasound, CT, or endoscopy does not exclude abdominal-wall or centrally mediated pain, but clinicians should investigate an organ problem before considering an intervention.
When is a nerve block appropriate, and which block matches the pain pattern?
A nerve block is appropriate when examination and imaging support a specific pain generator, not simply because scans are normal or pain persists.
| Option | What it targets | Pain pattern and role |
|---|---|---|
| Trigger-point injection | A small abdominal-wall focus | Tests and treats a tender nerve-entrapment point |
| Ilioinguinal nerve block | Ilioinguinal nerve | Groin, lower-abdominal, or post-hernia pain |
| Iliohypogastric nerve block | Iliohypogastric nerve | Lower-abdominal or suprapubic nerve pain |
| Transversus abdominis plane block | Nerves within the abdominal-wall plane | Broader abdominal-wall or post-surgical pain |
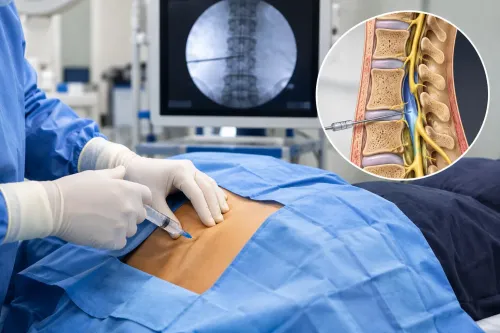
| Celiac plexus or splanchnic procedure | Upper-abdominal sympathetic pathways | Selected severe pain from advanced upper-abdominal cancer or carefully selected chronic pancreatitis |
| Superior hypogastric plexus procedure | Pelvic visceral sympathetic pathways | Pelvic or lower-abdominal visceral pain |
| Ganglion impar procedure | Terminal pelvic sympathetic pathway | Perineal, rectal, or pelvic pain |
A focal trigger-point injection can test suspected nerve entrapment as well as treat it. A temporary pain reduction of at least 50% supports that diagnosis; recurrence can still require reassessment rather than automatic repetition.
For chronic pancreatitis, clinicians must address a correctable obstructive cause before repeating blocks. Each procedure carries risks, including bleeding, infection, low blood pressure, and transient diarrhoea; rare neurological injury is also possible. Your examination, symptom pattern, and appropriate imaging must justify the target.
How does the underlying condition change the treatment goal?
The diagnosis sets the treatment goal, so one abdominal-pain procedure cannot suit every condition.
| Diagnosis | Main treatment goal | Why the procedure differs |
|---|---|---|
| Cancer-related abdominal pain | Improve comfort and function alongside disease treatment | A celiac plexus or splanchnic procedure may help selected severe upper-abdominal pain, but cancer care also requires oncology treatment and symptom support. |
| Chronic pancreatitis | Find and treat the pain generator | Assess duct obstruction, stones, or another structural cause before repeating nerve blocks. |
| Endometriosis | Treat pelvic disease and reduce pain linked to the cycle | Map pelvic symptoms and menstrual timing; a general abdominal injection will not treat endometrial lesions. |
| Irritable bowel syndrome | Reduce gut symptoms, pain amplification, and disability | Gut-directed therapy, activity planning, sleep support, and cognitive behavioural therapy often matter more than a block. |
| Inflammatory bowel disease | Control intestinal inflammation | Coordinate gastroenterology treatment; blocking pain without controlling inflammation can hide deterioration. |
| Post-surgical pain | Address scar, adhesion, abdominal-wall, or nerve pain | A focal injection or neuropathic treatment may fit better than a deep visceral procedure. |
| Centrally mediated or functional abdominal pain | Restore function and reduce pain amplification | Continuous pain with little relation to eating or defecation needs a broader rehabilitation and pain-management plan. |
Burning, electric shocks, numbness, allodynia, or pain from light touch can justify selected antidepressants or gabapentinoids, with individual monitoring for sedation and other adverse effects.
Opioids are not the default long-term treatment for chronic non-cancer abdominal pain. Constipation, sedation, dependence, overdose, and opioid-induced hyperalgesia can worsen function and obscure assessment; any use requires functional goals and regular review.
What should you ask for in a specialist pain-management plan?
A specialized pain evaluation adds value after urgent and organ-related causes have been assessed, especially when pain persists despite a normal scan. It should explain the suspected pain generator rather than use ongoing symptoms alone as a reason to perform a procedure.
1. Ask the clinician to review prior imaging, endoscopy, operations, injections, scars, focal sensory changes, bowel and bladder symptoms, and every medicine you take.
2. Ask how eating, movement, posture, and bowel movements change the pain. These details can point toward abdominal-wall, nerve, post-surgical, visceral, or centrally mediated pain.
3. Ask what pain generator is suspected and what evidence supports it. A normal ultrasound, CT, or endoscopy does not exclude abdominal-wall or nerve pain.
4. Agree on functional goals, such as walking farther, sleeping through the night, or returning to work. Pain intensity matters, but function shows whether treatment is helping.
5. If a block is proposed, ask why it is preferable to medication, rehabilitation, or disease-directed treatment, what result would support the diagnosis, and what risks require discussion.
Bring reports and a symptom diary to Spine And Pain Management Centre, which can provide this individualized specialist setting in Kalyan. The right next step may instead be medical, gastrointestinal, surgical, gynaecological, neurological, rehabilitative, psychological, or interventional care within multidisciplinary pain management.
Related service
Pain Treatment ₹700 Dr Prakash Deshmukh at Spine and Pain Management Centre in Kalyan provides advanced Sympathetic Block treatment for effective relief from cancer pain... View service → |
Frequently asked questions
Which chronic abdominal pain symptoms need emergency care first?
Seek emergency assessment for sudden severe or worsening pain, a rigid or swollen abdomen, fainting, persistent vomiting, vomiting blood, black stools, heavy bleeding, fever with marked illness, or possible pregnancy with pain or bleeding.
How do clinicians identify the source of chronic abdominal pain?
They combine your pain history and examination with medication review, bowel and urinary symptoms, prior surgery, blood or urine tests, imaging, and evaluation for abdominal-wall or nerve pain.
When is a nerve block appropriate for chronic abdominal pain?
A nerve block is considered when the pain pattern and examination point to a specific nerve or nerve group, such as abdominal-wall nerves, the coeliac plexus, or the superior hypogastric plexus.
How does the underlying condition change the treatment goal?
Treatment may target inflammation, cancer pain, nerve injury, scar-related pain, or abdominal-wall pain; goals can include treating the cause, improving movement and sleep, and reducing reliance on medicines.
What should you ask for in a specialist pain-management plan?
Ask for the working diagnosis, tests still needed, treatment options, expected benefits, risks, alternatives, medication changes, follow-up timing, and clear instructions for urgent symptoms.